Hematuria—the presence of red blood cells in the urine—is one of the most frequent clinical presentations in adult urology. Whether discovered visibly as red, pink, or cola-colored urine (gross hematuria) or detected incidentally during routine urinalysis (microscopic hematuria), blood in the urine serves as a cardinal warning sign that demands systematic diagnostic evaluation.
While hematuria often stems from benign conditions such as urinary tract infections (UTIs), benign prostatic hyperplasia (BPH), or kidney stones, it is also the primary presenting symptom of urothelial malignancies, including bladder cancer and upper tract urothelial carcinoma (UTUC). Historically, hematuria workups followed a one-size-fits-all model that frequently led to invasive testing for low-risk individuals or diagnostic delays for patients harboring early-stage malignancies.
Modern urologic practice utilizes evidence-based, risk-stratified diagnostic protocols to ensure thorough investigation while minimizing unnecessary interventions. In South Florida, Dr. Mourad Abouelleil is a board-certified urologist with the Palm Beach Health Network Physician Group, providing specialized care at Good Samaritan Medical Center in West Palm Beach and Palm Beach Gardens Medical Center. Having completed his medical training at the University of Wisconsin School of Medicine and Public Health and comprehensive residency training in urology at SUNY Upstate Medical University, Dr. Abouelleil combines high-definition flexible digital cystoscopy, multi-phase cross-sectional imaging, and advanced urinary genomic biomarkers to identify the underlying etiology of unexplained bleeding promptly.
Gross vs. Microscopic Hematuria: Understanding the Clinical Risk
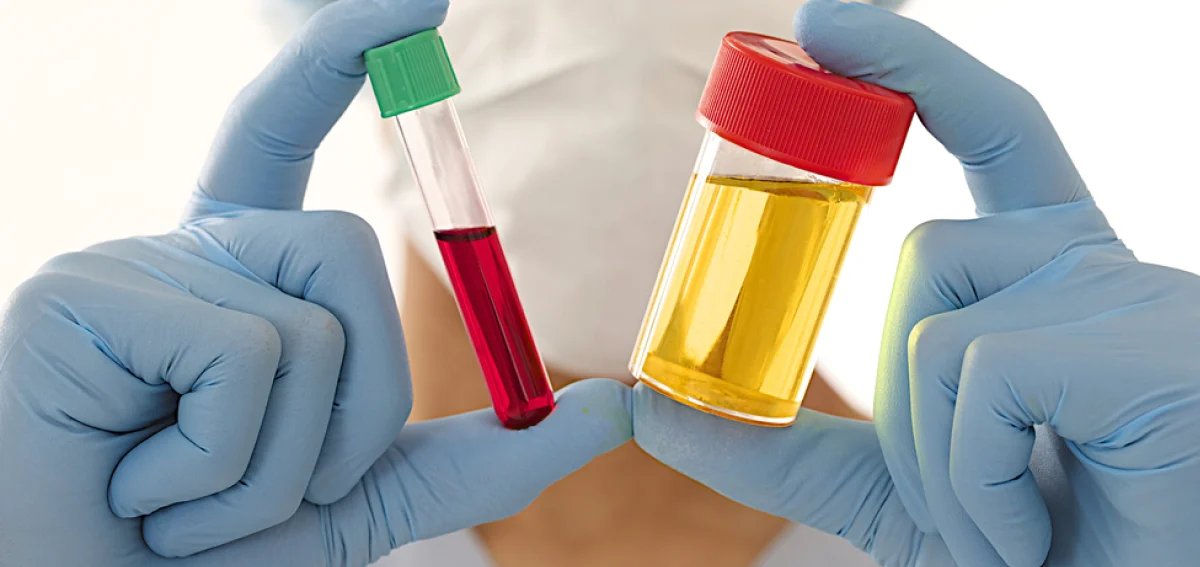
The visual appearance and concentration of blood cells in the urine directly influence the probability of uncovering an underlying malignancy:
- Gross Hematuria: Visible blood in the urine, with or without clots. Even a single episode of painless gross hematuria carries an estimated 10% to 20% risk of underlying urologic malignancy. Because gross bleeding can intermittently clear on its own as bleeding vessels temporarily seal, a single visible episode warrants a full urologic evaluation regardless of subsequent normal dipstick tests.
- Microscopic Hematuria: Urine that appears visibly clear to the naked eye but contains microscopic red blood cells. According to American Urological Association (AUA) guidelines, microscopic hematuria is formally defined as $\ge 3$ red blood cells per high-power field (RBC/HPF) on microscopic evaluation of properly collected centrifuged urine. Dipstick tests that register positive for blood without microscopic confirmation do not qualify as true hematuria and require formal laboratory microscopic verification.
The AUA Risk-Stratification Framework
The American Urological Association categorizes patients with microscopic hematuria into three distinct risk tiers based on their likelihood of harboring bladder or urothelial cancer:
- Low Risk: Women under 50 and men under 40 with no history of smoking, 3 to 10 RBC/HPF on urinalysis, and no additional urothelial cancer risk factors. Evaluation typically begins with repeat urinalysis in six months or shared decision-making regarding non-invasive testing.
- Intermediate Risk: Men aged 40 to 59 or women aged 50 to 59 with 11 to 25 RBC/HPF, or a smoking history between 10 and 30 pack-years. These patients are recommended for cystoscopy and renal ultrasound to evaluate the bladder and kidneys.
- High Risk: Anyone with gross hematuria, age 60 or older, a smoking history exceeding 30 pack-years, occupational exposure to aromatic amines/dyes (e.g., painters, machinists, textile workers), persistent hematuria $> 25\text{ RBC/HPF}$, or irritative voiding symptoms (urinary urgency, frequency, dysuria) without infection. High-risk patients require comprehensive evaluation consisting of cystoscopy and multiphasic CT urography.
The Diagnostic Triad: The Comprehensive Workup
Evaluating hematuria requires examining both the lower urinary tract (urethra and bladder) and the upper urinary tract (ureters and kidneys):
1. High-Definition In-Office Flexible Cystoscopy
Cystoscopy is the diagnostic gold standard for visualizing the lower urinary tract. Modern flexible cystoscopes utilize ultra-slim, pliable insertion tubes with digital chip-on-the-tip cameras:
- The Experience: Performed in the office under local anesthetic lubricating gel (lidocaine), the procedure takes approximately three to five minutes. Patients experience minimal discomfort and can watch the high-definition monitor alongside the physician.
- The Anatomy: Dr. Abouelleil inspects the anterior and posterior urethra, the prostate gland in men, the entire inner lining (urothelium) of the bladder, the ureteral orifices, and the bladder dome. Subtle papillary tumors, flat reddish patches indicative of carcinoma in situ (CIS), and benign sources such as bleeding prostate veins or bladder stones are directly visualized.
2. Upper Tract Cross-Sectional Imaging
Because cystoscopy evaluates only the bladder and urethra, imaging is necessary to assess the kidneys and ureters:
- Multiphasic CT Urography (CTU): The preferred diagnostic standard for high-risk patients. It includes non-contrast imaging (to detect kidney and ureteral stones), a nephrographic phase (to evaluate solid renal tumors), and an excretory phase (where contrast fills the collecting system and ureters to outline filling defects such as upper tract urothelial cancers).
- Renal Ultrasound or MR Urography: Utilized for intermediate-risk individuals or patients with impaired kidney function or severe iodinated contrast allergies who cannot safely undergo contrast-enhanced CT scans.
3. Urinary Cytology and Molecular Biomarkers
Urine analysis provides complementary microscopic and genetic information:
- Voided Urine Cytology: Pathological review of shed transitional cells. While highly specific for high-grade bladder cancer and CIS, cytology has low sensitivity for detecting low-grade papillary tumors.
- Non-Invasive Genomic Urine Assays (e.g., Cxbladder®, UroVysion® FISH): Molecular assays that measure mRNA gene expression or chromosomal abnormalities in shed urothelial cells. These biomarkers assist in adjudicating indeterminate cystoscopy findings and help stratify intermediate-risk patients to determine whether invasive testing can be avoided.
Comparative Overview: Diagnostic Modalities in Hematuria Evaluation
| Diagnostic Tool |
Target Anatomical Region |
Clinical Strength |
Diagnostic Limitation |
| Flexible Office Cystoscopy |
Urethra & Bladder |
Gold standard for lower tract tumors; direct visualization |
Cannot visualize ureters or kidneys |
| Multiphasic CT Urogram (CTU) |
Kidneys & Ureters (Upper Tract) |
High sensitivity for small stones & upper tract tumors |
Radiation exposure & iodinated contrast |
| Renal Ultrasound |
Kidneys & Distal Bladder |
Zero radiation; evaluates hydronephrosis & cysts |
Poor sensitivity for small ureteral tumors |
| Urine Cytology |
Entire Urothelium (Shed cells) |
High specificity for aggressive high-grade CIS |
Low sensitivity for low-grade tumors ($< 40\%$) |
| Molecular Biomarkers (mRNA) |
Entire Urothelium (Genomic) |
High negative predictive value ($> 95\%$) |
Can yield false positives in active infection |
What Happens When a Bladder Tumor is Identified?
If flexible cystoscopy reveals an abnormal papillary mass, sessile growth, or suspicious velvety erythematous plaque, definitive surgical staging is scheduled:
- Surgical Resection (TURBT): Dr. Abouelleil schedules a formal outpatient procedure known as a Transurethral Resection of Bladder Tumor (TURBT) under general or spinal anesthesia.
- Histopathological Staging: Using an operative resectoscope, the visible tumor is resected alongside the underlying detrusor muscle layer. This enables the pathologist to determine both the tumor grade (low grade vs. high grade) and the tumor stage—distinguishing non-muscle invasive bladder cancer (NMIBC) from muscle-invasive bladder cancer (MIBC), which dictates subsequent treatment and surveillance protocols.
Conclusion & Practice Information
Blood in the urine should never be ignored or assumed to be an innocent consequence of vigorous exercise, mild dehydration, or a simple infection without confirmatory follow-up. Through risk-stratified protocols, gentle in-office flexible cystoscopy, and advanced diagnostic imaging, Dr. Mourad Abouelleil provides patients with clear answers and early detection when urologic conditions are most treatable.
- Surgeon: Dr. Mourad Abouelleil, MD
- Board Certification: American Board of Urology
- Practice Group: Urology Medical Associates – Palm Beach Health Network Physician Group
- Hospital Affiliations: Good Samaritan Medical Center (West Palm Beach) & Palm Beach Gardens Medical Center
- Primary Office Locations:
- West Palm Beach: 1411 North Flagler Drive, Suite 3800, West Palm Beach, FL 33401
- Jupiter: 641 University Boulevard, Suite 105, Jupiter, FL 33458
- Port St. Lucie: 900 Southeast Becker Road, Port St. Lucie, FL 34984
- Office Consultations: (561) 291-7182